51
JFK Assassination Discussion & Debate / Re: The future of the Republican Party
« Last post by Tom Graves on Yesterday at 06:08:15 AM »“WHOEVER WINS JFK, WINS !!”
————————————Napoleon Solie, secret agent
You're so cute.

 Recent Posts
“WHOEVER WINS JFK, WINS !!”
————————————Napoleon Solie, secret agent
From the outset, the Dallas doctors’ and nurses’ descriptions of JFK’s throat wound have posed a problem for the lone-gunman theory. All the descriptions of the throat wound described it as an entrance wound. They said it was a small wound (about 5 cm in diameter), that it was punched inward, and that it was neat and circular, all of which are textbook indications of an entry wound. In addition, the descriptions of the damage behind the wound described damage that was larger than the wound itself, another textbook indication of an entry wound.
This explains why Dr. Malcolm Perry diagnosed the throat wound as an entry wound (both in his written report and in his comments to newsmen later in the afternoon), and why Nurse Margaret Hinchliffe, who had seen numerous bullet wounds, was certain it was an entry wound.
It is important to note that the fact that the throat wound was 5 mm in diameter means it was smaller than the back wound, which was 6 x 4 mm in size.
In addition, we now know that the first two drafts of the autopsy report said nothing about the throat wound being an exit point for the back wound. Indeed, we also know that one of those drafts said the back wound had no exit point.
In order to explain the throat wound’s entry-wound appearance, lone-gunman theorists have had to resort to theorizing that the wound was so small and neat because the skin behind and around the wound was “shored” by the fabric of JFK’s collar band.
There are two fatal problems with this shored-wound theory:
-- One, the throat wound was not behind the collar band. Even if one assumes the front shirt slits were made by an exiting bullet, those slits were clearly below the collar band, as proved by the evidence photo of the slits (see Figure 8 in “JFK’s Clothing Proves the Single-Bullet Theory Is Impossible,” https://drive.google.com/file/d/1MAgWA0frOLVeWY6ok9nzdrgpRN4Wv1AL/view).
-- Two, shored exit wounds, far from being small and neat, typically have wide and irregular abrasion collars. Dr. Vincent Di Maio, considered one of the leading forensic experts of the modern era, noted that shored exit wounds produce “very wide, irregular abrasion collars” (Gunshot Wounds: Practical Aspects of Firearms, Ballistics, and Forensic Techniques, Second Edition, CRC Press, 1999, p. 112).
Dr. Gary Aguilar and RN Kathy Cunningham have said the following about the problems with the shored-wound theory:
Lattimer has theorized that Kennedy’s throat wound was so small because it was “shored.” That is, Kennedy’s tight shirt collar confined the skin around Kennedy’s throat, and so kept the tissues from gaping irregularly as the bullet exited. . . . However, the slits in JFK’s shirt are below the level where the collar button is, and so below the spot where the shoring pressures would have had maximal effect in limiting the gaping of skin.
Information from experiments on more analogous living pigs, and from experience with living gunshot victims, reveals that there are key features of shored exit wounds that are notable by their absence in JFK’s throat. Anesthetized pigs shot through their “shored” bellies had abrasions (scratches) at the margins of the shored exit wounds 100% of the time; contusions (bruises) 63% of the time; and radiating lacerations around the wound margins 33% of the time (D.S. Dixon, “Characteristics of Shored Exit Wounds,” Journal of Forensic Sciences, vol. 26(4), 1981, p. 694). Forensic pathologist Josephino Aguilar (no relation to either author) reported that, in humans, shored exit wounds have “abrasion collars” much like entrance wounds do, and they tend to have “radiating lacerations” at the wound margins. “In contrast to the entrance wound,” Aguilar wrote, “the supported exit wound shows a scalloped or punched-out abrasion collar and sharply contoured skin in between the radiating skin lacerations marginating the abrasion” (Josephino C. Aguilar, “Shored Gunshot Wounds of Exit,” American Journal of Forensic Medicine and Pathology , vol. 4(3), September 1983, p. 199). (“How Five Investigations Into JFK’s Medical/Autopsy Evidence Got It Wrong,” https://history-matters.com/essays/jfkmed/How5Investigations/How5InvestigationsGotItWrong_6.htm)
For more information on this issue, see “Research Notes on the Shored-Wound Theory to Explain JFK’s Throat Wound,” https://drive.google.com/file/d/1h48FpT89KrC0rNrl4XC3MDePLDFEBBHb/view.
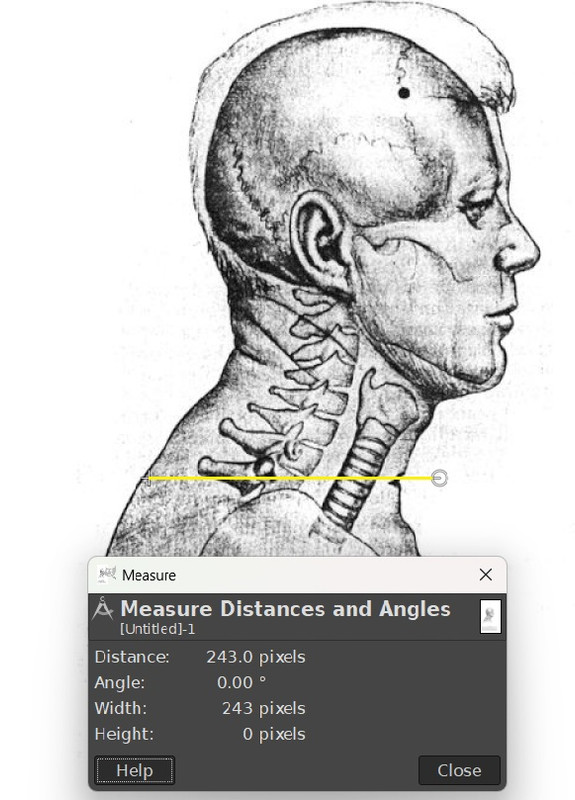
You realize that T1 was below the throat wound, right? Right? Look at the FPP's SBT diagram
The Innocence Project has used DNA and other forensic evidence to exonerate people convicted primarily on the basis of eyewitness testimony. Juries tend to give eyewitness testimony for more weight than it deserves.The Innocence Project has been successful in setting aside convictions based on mistaken eyewitness identification evidence. Eyewitness identification evidence is not fact observation unless the witness knows the person and recognizes them at the time of the offence. There are also serious problems with ensuring the evidence is not contaminated with bias of the official conducting a photo or in-person line up.
You again blunder over information that has been known for decades. First off, you realize that the term "several" can refer to as many as nine or 10, right? You can Google it.
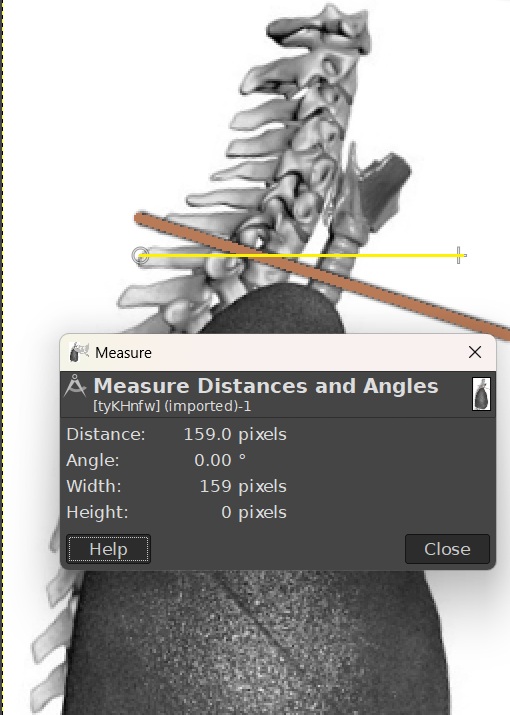
If a majority of the FPP disagreed with the upward-trajectory finding, why does the FPP's SBT diagram (7 HSCA 100, Figure 12) show the bullet traveling upward through the neck and show JFK leaning substantially forward? Why did Dr. Baden, the FPP chairman, demonstrate an upward trajectory through the neck with a wooden pointer in his filmed interview for NOVA's 1988 JFKA documentary, and why did Baden then lean markedly forward, still holding the pointer, to show how an upward trajectory through the neck could line up with the sixth-floor window? And, why does the FPP's report say that the back wound's abrasion collar is "evidence that the bullet's trajectory at the instant of penetration was slightly upward in relation to the body"? Let's read what the FPP said on this issue:
A red-brown to black area of skin surrounds the wound, forming what is called an abrasion collar. It was caused by the bullet's scraping the margins of the skin on penetration and is characteristic of a gunshot wound of entrance. The abrasion collar is larger at the lower margin of the wound, evidence that the bullet's trajectory at the instant of penetration was slightly upward in relation to the body. (7 HSCA 175)
Of course, one major problem is that no photo or frame shows JFK leaning as far forward as the FPP and Baden had to assume he was.
Uh, yes, I already pointed this out. You realize that T1 was below the throat wound, right? Right? Look at the FPP's SBT diagram (7 HSCA 100, Figure 12). Here's a link to it:
https://fr.wikipedia.org/wiki/Fichier:HSCA-JFK-neck2-6-43.jpg
Notice that the diagram shows the bullet entering slightly below the throat wound. Why do you suppose that not a single pro-SBT diagram acknowledges the FPP's location for the back wound and the FPP's depiction of an upward trajectory through the neck? Humm? Why do you suppose that is?
What?! The drawing was made under Humes's direction and instruction. The medical artist, Harold Rydberg, only drew what Humes told him to draw; Humes presented the drawing to the WC as an accurate depiction of the SBT's trajectory through the neck; and the WC cited the drawing three times in the Warren Report and published it as an exhibit. The drawing, CE 385, shows the back wound above the throat wound and has the bullet traveling downward through the neck.
And every single pro-SBT trajectory illustration, from Lattimer's diagrams to Myers' fraudulent animation, erroneously has the mythical magic bullet traveling downward through JFK's neck.
T1 is not in the "low neck." The neck ends at C7. The "C" stands for "cervical." The "T" stands for "thoracic." The FPP correctly referred to the T1 location as being "in the back area" and noted it was "a few inches lower" than where Humes placed it in CE 385 (1 HSCA 256).
It is just incredible that you guys still refuse to deal with the fact that the only way to make the T1 location and its upward trajectory work for the SBT is to make the demonstrably false assumption that JFK was leaning markedly forward when the bullet struck.
Your denial of obvious reality here is akin to your long-standing refusal to acknowledge the fact that JFK's clothing clearly, self-evidently refutes any notion that the back-wound bullet exited the throat. Objective people can read your grasping replies in my threads "JFK's Clothing Refutes the Single-Bullet Theory" and "JFK's Throat Wound Was an Entrance Wound: Refuting the Shored-Wound Theory" and see that you guys have no tenable, sensible explanation for the clothing evidence.

If you guys were dealing rationally and credibly with the evidence, you would have abandoned the SBT way back when we learned (1) that there was no hole through JFK's tie and no nick on either edge of the tie knot, and (2) that the bullet holes in the back of JFK's shirt and coat were over 5 inches below the collar.
Incorrect. Some cases are built entirely on witness evidence.Incorrect. It depends on the ability of a human to accurately observe. Besides, the sound source witnesses were not consistent, varying with their location. You keep using the witbesses who were asked about where they thought the shot sounds originated. The only ones who felt reasonably sure about the source direction were close to the TSBD and even many of those were not sure. Give us an example of where the witnesses were generally consistent and demonstrably wrong.